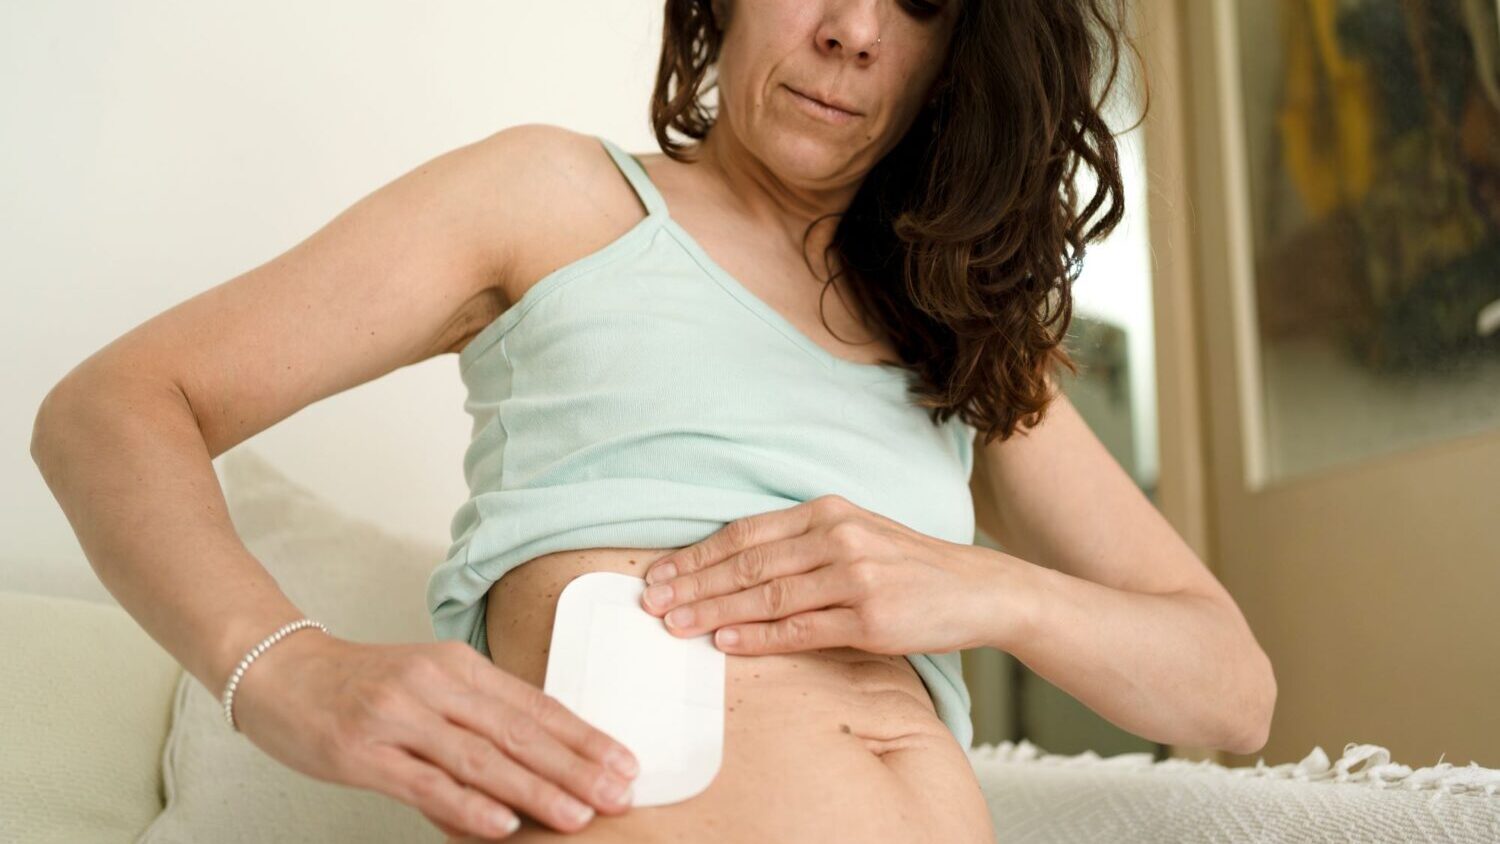
The U.S. Food and Drug Administration (FDA) has removed language regarding the risks of breast cancer, cardiovascular disease, and dementia from the boxed warnings—the agency’s strongest safety notices—on three transdermal menopause hormone patches. The regulatory update follows a comprehensive reassessment of warnings established over two decades ago based on findings from a landmark clinical trial. However, the FDA maintained strict contraindications prohibiting use among women with a personal history of breast cancer or blood clotting disorders.
The U.S. Department of Health and Human Services announced on October 30 that the FDA approved updated labeling for three estradiol patch formulations: Minivelle, Vivelle, and Vivelle-Dot. The action follows similar labeling modifications applied to six other hormone therapy products in February.
Revisiting the 2002 Women’s Health Initiative Data
Menopausal hormone therapy is prescribed to alleviate systemic symptoms such as hot flashes and night sweats caused by declining estrogen levels, as well as to prevent osteoporosis. Safety concerns surrounding these therapies escalated in 2002 following the publication of the Women’s Health Initiative (WHI) study, which evaluated an oral combination of estrogen and progestin in 16,608 postmenopausal women with an intact uterus.
In that trial, participants receiving combined oral hormone therapy exhibited a 26% relative increase in breast cancer risk compared to placebo after an average follow-up of 5.2 years, along with a 41% increase in stroke risk and a 29% increase in coronary heart disease. In absolute terms, a 26% relative risk increase represented approximately eight additional cases of breast cancer per 10,000 women annually. Citing an overall risk-benefit imbalance, researchers halted the trial prematurely.
A secondary WHI study published in 2004 evaluated 10,739 hysterectomized women taking oral estrogen alone. While stroke risk increased by 39% over an average of 6.8 years, researchers observed no statistically significant increase in breast cancer risk.
Medical experts subsequently noted major limitations in generalizing the WHI findings across all menopausal populations. The original trial utilized oral formulations in a cohort with an average age of 63—significantly older than the typical age of menopause onset. Subsequent observational studies indicated that transdermal estradiol applied to the skin carries a lower risk of venous thromboembolism than oral estrogens. Following an evaluation of long-term observational data, the FDA updated patch labeling to distinguish risks based on age at treatment initiation, route of administration, and individual cardiovascular health.

Critical Safety Exclusions, Guidelines, and Monitoring Protocols
Despite the revised warning labels, transdermal hormone patches remain contraindicated for several patient groups. Under the updated labels, women with a active or prior history of breast cancer, deep vein thrombosis, pulmonary embolism, stroke, or myocardial infarction cannot use the patches. Absolute contraindications also include unexplained vaginal bleeding, underlying severe clotting disorders, and active liver disease.
The FDA continues to emphasize the necessity of baseline breast cancer risk assessments prior to initiating therapy, alongside routine clinical breast examinations and mammography screening during treatment. For women with an intact uterus, unopposed estrogen therapy stimulates endometrial proliferation, significantly elevating the risk of endometrial cancer. Consequently, co-administration of progestin is required to protect the uterine lining, and the FDA retained its strongest boxed warning regarding endometrial cancer risk.
The clinical risk-benefit profile of hormone therapy varies substantially according to when treatment begins. Updated clinical guidelines released in October by the American College of Obstetricians and Gynecologists (ACOG) recommend hormone therapy for women under age 60 or within 10 years of menopause onset who suffer from bothersome vasomotor symptoms and lack contraindications, as benefits are most likely to outweigh potential risks during this window. Conversely, initiating systemic hormone therapy after age 60 or more than a decade post-menopause warrants heightened clinical caution due to elevated baseline cardiovascular and cerebrovascular risks.
Patients receiving treatment must remain vigilant for potential warning signs. Sudden unilateral weakness or slurred speech requires immediate emergency evaluation for stroke, as do severe chest pain, acute dyspnea, or unilateral lower-extremity swelling and tenderness. Any postmenopausal vaginal bleeding, regardless of volume, requires prompt medical evaluation to rule out endometrial pathology.
For patients experiencing localized symptoms such as vaginal dryness or dyspareunia without systemic hot flashes, low-dose local vaginal estrogen or non-hormonal therapeutic options may be considered. Ultimately, decisions regarding menopausal hormone therapy require individual risk stratification considering age, time since menopause, uterine status, and personal oncologic and cardiovascular history.